






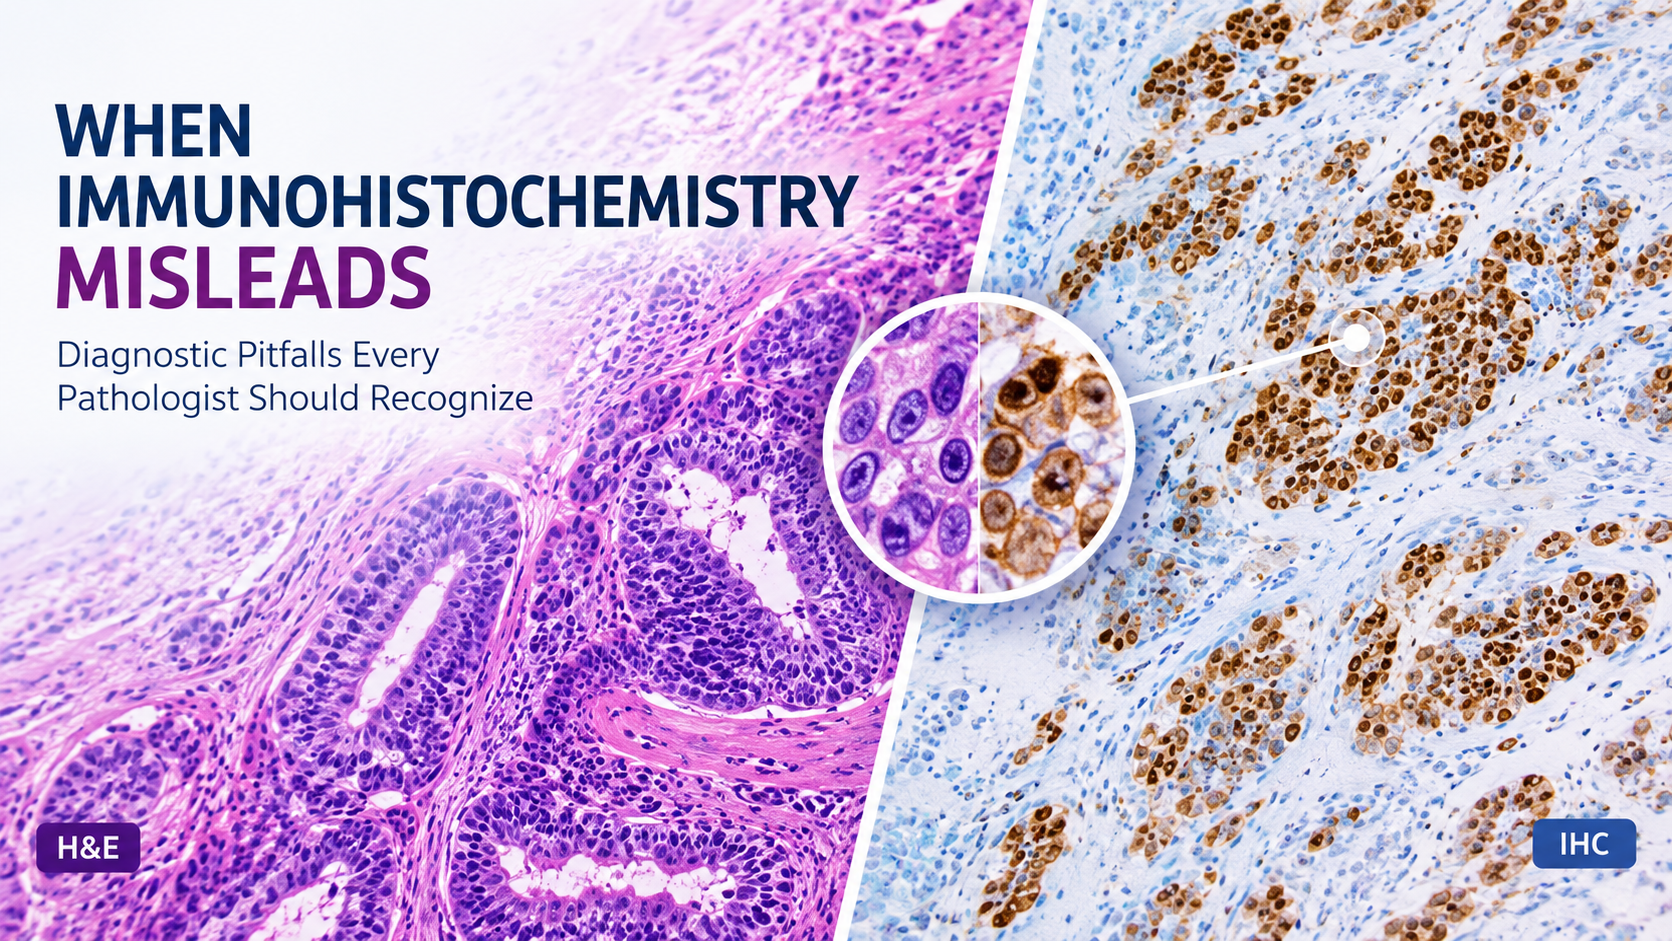
Immunohistochemistry (IHC) has transformed diagnostic pathology by helping characterize cells, establish lineage, distinguish morphologically similar entities, and refine difficult differential diagnoses. Yet even a technically successful stain can be diagnostically misleading when its expression pattern is interpreted without sufficient morphological and clinical context.
A positive marker does not automatically establish a diagnosis. A negative result does not necessarily exclude an entity. Unexpected staining may reflect technical limitations, biological variation, aberrant antigen expression, or an incorrect assumption about what a particular marker can demonstrate.
For practicing pathologists, the challenge is not simply selecting the right antibody. It is understanding what the stain demonstrates, what it cannot establish, and whether the result fits the tissue under examination.
This article explores common immunohistochemistry pitfalls, the reasoning errors that can arise during interpretation, and practical principles for integrating immunophenotypic findings into a defensible diagnosis.
1. The Fundamental Principle: Morphology Comes First
Immunohistochemistry is most informative when it answers a specific question generated by morphological examination.
The architectural pattern, cytological features, distribution of the lesion, stromal relationship, and background inflammatory or non-neoplastic components help establish the differential diagnosis. IHC can then provide additional evidence to support or challenge the leading possibilities.
Problems arise when marker selection precedes adequate morphological assessment or when an isolated stain is allowed to dominate the interpretation.
For example, a marker associated with a particular cellular lineage may also be expressed in selected unrelated neoplasms or non-neoplastic cell populations. Its presence therefore needs to be interpreted alongside morphology, staining distribution, intensity, and the behavior of other markers.
A useful diagnostic sequence is:
- Establish the morphological differential diagnosis.
- Define the specific question that requires immunohistochemical clarification.
- Select markers based on their diagnostic utility and limitations.
- Evaluate staining in the correct cellular population.
- Integrate the findings with morphology and relevant clinical information.
- Reconsider the differential when the results are discordant.
The purpose of IHC is not to replace morphological reasoning. It is to make that reasoning more discriminating.
2. Technical Pitfalls: When the Stain Does Not Reflect the Biology
Before interpreting an unexpected immunophenotype, pathologists must consider whether the staining result reliably represents antigen expression in the tissue.
Pre-analytical and analytical variables can affect immunoreactivity. These include fixation conditions, tissue processing, decalcification, antigen retrieval, antibody performance, detection chemistry, and the condition of the tissue section.
Fixation and tissue processing
Delayed fixation, inadequate fixation, or prolonged exposure to fixative can affect antigen preservation. The degree and direction of the effect vary according to the antigen, tissue, and processing conditions.
A weak or absent stain may therefore reflect reduced antigen detectability rather than true biological absence.
This distinction becomes especially important when a negative result would substantially alter the differential diagnosis or determine whether additional testing is required.
Antigen retrieval and staining conditions
Antigen retrieval is designed to improve the accessibility of target epitopes, but the optimal conditions are not identical for every antibody.
Inappropriate retrieval conditions, reagent problems, or deviations from validated protocols can compromise staining performance. Excessive background, unexpectedly weak labeling, and inconsistent results may indicate technical problems that require investigation.
Tissue quality and artifacts
Crush artifact, necrosis, tissue degeneration, edge effects, and other morphological distortions can complicate the assessment of staining patterns.
The pathologist should determine whether the cells being evaluated are sufficiently preserved and whether the observed staining is reproducible and interpretable.
Practical principle: An unexpected result should trigger an assessment of technical validity before it is treated as evidence of an unusual biological phenotype.
3. Internal Controls: The Importance of Knowing What Should Stain
Internal controls are particularly valuable because they help assess whether the staining reaction has worked appropriately within the tissue section itself.
Depending on the marker and specimen, recognizable non-target cells may provide useful positive or negative control information. External controls provide complementary evidence that the staining procedure performed as expected.
However, controls must be appropriate to the antibody and intended interpretation. The presence of a positive internal control does not automatically establish that every target cell has preserved antigenicity, nor does a negative internal control necessarily invalidate every possible result.
Pathologists should evaluate:
- Whether the expected control population is present.
- Whether the control demonstrates the anticipated staining pattern.
- Whether the target tissue is adequately preserved.
- Whether background staining interferes with interpretation.
- Whether the observed result is consistent with the validated assay characteristics.
Controls are not merely laboratory quality checks. They are part of the evidence used to decide whether an immunohistochemical result can be interpreted confidently.
4. Aberrant Antigen Expression: When Cells Break the Expected Rules
One of the most challenging interpretive problems occurs when a neoplasm demonstrates an immunophenotype that differs from its expected pattern.
Lineage-associated markers are useful because they reflect biological differentiation. However, antigen expression is not always exclusive to a single lineage, and some neoplasms may acquire unexpected markers or lose markers that would ordinarily be expected.
This phenomenon is particularly relevant in hematolymphoid pathology, where aberrant expression can complicate lineage assignment and classification.
An unexpected marker should not automatically override the overall morphological and immunophenotypic pattern.
Instead, the pathologist should consider:
- Whether the marker is genuinely expressed by the lesional cells.
- Whether the staining pattern and intensity are compatible with the assay’s validated interpretation.
- Whether the marker has recognized expression in other cell types or disease categories.
- Whether the remaining markers support the proposed lineage.
- Whether additional studies are necessary to resolve the discrepancy.
Aberrant expression is not necessarily evidence of technical failure. It may represent genuine biological variation. The important task is distinguishing an unusual but valid phenotype from an unreliable or incorrectly interpreted result.
5. Positive Staining Does Not Always Mean Diagnostic Specificity
A common interpretive trap is equating positivity with specificity.
Many antibodies demonstrate useful sensitivity for particular diagnostic categories but have limitations in distinguishing those categories from their mimics. A marker may be frequently expressed in a particular entity while also occurring in other neoplasms or normal cellular populations.
The diagnostic value of a stain therefore depends on the question being asked.
Consider three separate questions:
- Is the marker present? This establishes whether the target is detectable under the assay conditions.
- Which cells express it? This establishes whether staining belongs to the lesional population or to background cells.
- What does the expression establish diagnostically? This requires assessment of specificity, morphology, the differential diagnosis, and the combined evidence.
These questions are related, but they are not interchangeable.
The distribution of staining may be just as important as its presence. Nuclear, membranous, or cytoplasmic localization must be assessed according to the marker’s intended interpretation. Focal, diffuse, weak, and strong expression may also have different significance depending on the antibody and diagnostic context.
There is no universal rule that diffuse staining is always meaningful or focal staining is always insignificant. Interpretation must follow the validated criteria for the specific marker and application.
6. Negative Results: Absence of Staining Is Not Always Absence of the Target
Negative staining can be diagnostically useful, but it must be interpreted cautiously.
A negative result may reflect true absence of the antigen, expression below the assay’s detection threshold, technical limitations, tissue heterogeneity, or loss of the relevant cell population in the section.
The significance of a negative stain depends on the sensitivity of the assay, the expected expression pattern, and the clinical and morphological context.
Before using a negative result to exclude a diagnostic possibility, consider:
- Was the specimen adequately fixed and processed?
- Were appropriate controls satisfactory?
- Was the target population adequately represented?
- Is the marker consistently expressed in the entity under consideration?
- Could heterogeneous expression or sampling limitations explain the result?
- Would an alternative marker or complementary test provide more reliable evidence?
A negative stain should modify the differential diagnosis according to the strength of the evidence, rather than automatically eliminate a possibility.
7. Marker Panels: Why More Stains Do Not Automatically Mean More Certainty
When a diagnosis is difficult, it may be tempting to order a large panel of immunostains. Although expanded panels can be useful in selected cases, indiscriminate testing introduces its own problems.
Additional stains consume tissue, increase cost, create more opportunities for equivocal findings, and may complicate interpretation when the results are not evaluated within a coherent diagnostic framework.
A better approach is to use a hypothesis-driven panel.
Each marker should address a defined question: lineage, differentiation, exclusion of a relevant mimic, or clarification of a specific morphological feature.
The panel should be designed so that the combined findings can distinguish the principal alternatives. Marker selection should also consider the availability of tissue for molecular studies or other ancillary investigations that may be required later.
When results conflict, adding more markers without reconsidering the original hypothesis may simply produce a larger set of unexplained findings.
The objective is not to maximize the number of stains. It is to obtain the most informative evidence needed to resolve the diagnostic question.
8. The Discordant Case: When Morphology and IHC Do Not Agree
A particularly important moment in diagnostic practice occurs when the immunophenotype appears inconsistent with the morphology.
Imagine a biopsy showing a distinctive architectural and cytological pattern, but the initial immunohistochemical panel does not support the leading morphological interpretation.
There are several possible explanations:
- The initial morphological impression requires revision.
- The lesional cells have an unusual or aberrant phenotype.
- One or more stains are technically unreliable.
- The marker panel does not adequately distinguish the relevant alternatives.
- The tissue sample is limited or unrepresentative.
- The differential diagnosis needs to be expanded.
The correct response is not to force the morphology and immunophenotype into agreement.
Instead, reassess the case systematically. Review the hematoxylin and eosin section, verify the cells being evaluated, examine the controls, confirm the staining patterns, and reconsider the assumptions underlying the initial panel.
Depending on the case, appropriate next steps may include repeat staining, additional targeted markers, deeper sections, expert consultation, or molecular testing.
The appropriate investigation depends on the specimen, the differential diagnosis, the available evidence, and the intended diagnostic classification.
Discordance is not merely an inconvenience. When recognized and investigated systematically, it can reveal a limitation in the original hypothesis or expose a problem that would otherwise remain unresolved.
9. Avoiding Cognitive Bias in Immunohistochemical Interpretation
Technical accuracy alone does not eliminate interpretive error. Diagnostic reasoning can also be influenced by cognitive biases.
Anchoring bias occurs when an initial impression receives disproportionate weight, even after contradictory evidence emerges.
Confirmation bias occurs when findings that support a favored diagnosis receive more attention than findings that challenge it.
Premature closure occurs when the diagnostic process stops before reasonable alternatives have been adequately considered.
IHC can unintentionally reinforce these tendencies. Once a particular diagnosis is suspected, a positive associated marker may appear more convincing than it would in another context, while discordant findings may be dismissed as exceptions.
Several practices can help reduce these risks:
- Document the leading differential before selecting the panel.
- Define what result would support or challenge each possibility.
- Evaluate each stain independently before integrating the panel.
- Give contradictory findings explicit consideration.
- Seek a second opinion when significant uncertainty remains.
- Revisit the diagnosis when new evidence changes the original assumptions.
These approaches do not eliminate uncertainty, but they make the reasoning process more transparent and reproducible.
10. Building a Reliable IHC Quality Framework
Consistent immunohistochemical interpretation requires collaboration between the diagnostic pathologist and the laboratory team responsible for assay performance.
A robust quality framework includes validated procedures, appropriate controls, reagent and instrument monitoring, documented troubleshooting, and review of unexpected staining patterns.
Laboratories should also establish processes for investigating discordant results and documenting corrective actions when technical problems are identified.
Useful quality indicators may include staining failure rates, repeat testing, control failures, turnaround time for resolving technical problems, and recurring patterns of interpretive disagreement.
Such measures should be evaluated in context rather than treated as isolated performance targets. For example, an increase in repeat staining may reflect a genuine technical problem, a change in case complexity, or a deliberate improvement in quality assurance.
Quality improvement is most effective when it identifies the underlying cause of a problem and addresses it systematically.
Conclusion: Interpret the Evidence, Not Just the Stain
Immunohistochemistry is an essential component of modern diagnostic pathology, but its value depends on disciplined interpretation.
Technical artifacts, unexpected antigen expression, limited marker specificity, false-negative results, and discordance with morphology can all complicate diagnostic assessment.
The most reliable approach combines morphological examination, technically valid staining, appropriate controls, carefully selected marker panels, and critical evaluation of contradictory evidence.
For pathologists, the key question is not simply whether a stain is positive or negative. It is whether the result provides credible, relevant evidence for the diagnosis being considered.
Recognizing the limitations of immunohistochemistry is not a weakness in diagnostic practice. It is an essential part of using the technique responsibly.
At Onward Assist, we support the pathology community through content focused on diagnostic reasoning, laboratory practice, and developments in pathology. Explore our Resources section for more insights into the evolving science and practice of pathology.
Further Reading
- Bussolati G, Leonardo E. Technical pitfalls potentially affecting diagnoses in immunohistochemistry. Journal of Clinical Pathology. Read the article.
- Miller RT. Avoiding pitfalls in diagnostic immunohistochemistry—important technical aspects that every pathologist should know. Seminars in Diagnostic Pathology. 2019. View the publication.
- Song JY, Pan Z. Aberrant expression in lymphoma, a diagnostic pitfall. Human Pathology. 2025. View the publication.
Editorial note: This article is intended for professional education and discussion. It does not replace assay-specific validation, current classification criteria, or case-specific clinical and pathological judgment.
